The Role of Bone Grafting in Dental Implants
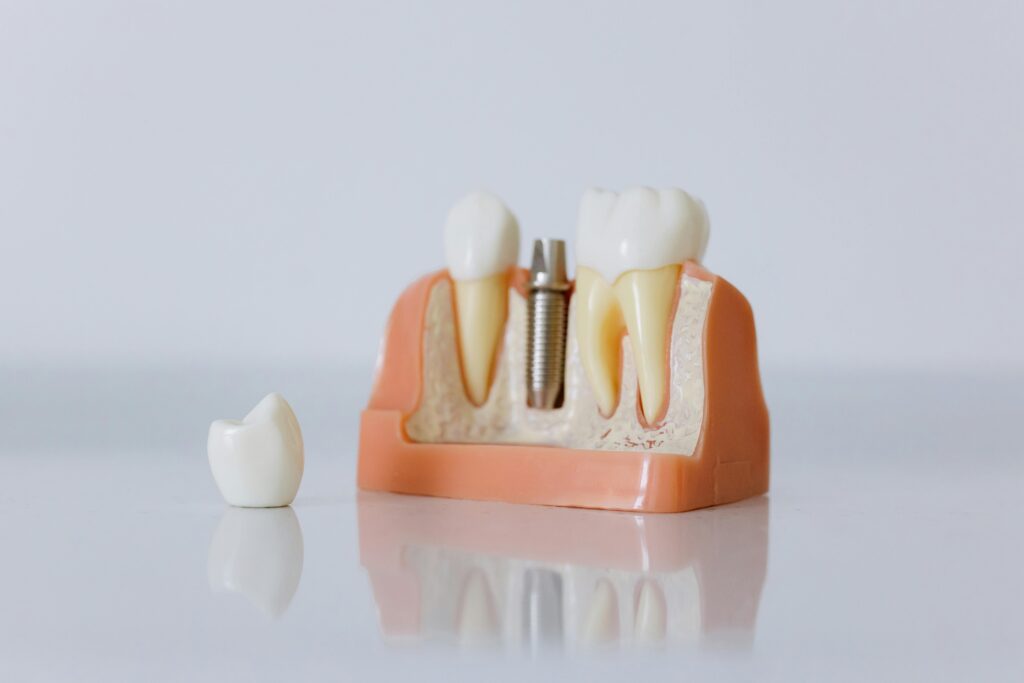
Dental implants depend on something very simple and very unforgiving: bone. The implant itself is a titanium or ceramic fixture placed into the jaw, but its long-term success rests on the body’s ability to anchor that fixture in healthy, stable bone. When enough bone is not present, or when the quality of the bone has been compromised, bone grafting often becomes part of the treatment plan.
For many patients, that recommendation comes as a surprise. They assume the missing tooth is the problem and the implant is the answer. Clinically, it is rarely that tidy. By the time a patient is ready to replace a tooth, the jawbone in that area may already have started to shrink. If the tooth was lost years ago, if there was a periodontal infection, if a denture has pressed on the ridge for a long time, or if trauma damaged the socket, the site may no longer have the width or height needed to place an implant predictably.
Bone grafting exists to rebuild that foundation. It is not an extra procedure added for convenience or revenue. In well-selected cases, it is what makes implant treatment possible, safer, and more durable.
Why bone disappears after a tooth is lost
The jaw is a living structure. It remodels according to use. Natural tooth roots transmit chewing forces into the surrounding bone, which helps maintain its volume and density. Once a tooth is removed, that stimulation drops sharply. The body begins to resorb, or break down, the bone that once held the root.
This change can happen faster than many people expect. The most significant loss often occurs in the first several Dental Implants months after extraction, though remodeling continues over time. In practical terms, the ridge may become narrower, shorter, and less able to support a properly sized implant. In the upper back jaw, the maxillary sinus may also expand downward, reducing available bone height. In the lower jaw, anatomy such as the inferior alveolar nerve limits how deeply an implant can be placed, which makes every millimeter of remaining bone matter.
A patient may look in the mirror and see a gap. A surgeon looking at a scan may see a thin ridge with a concavity on the facial side, or a site where the socket walls collapsed after a difficult extraction. Those details shape treatment far more than patients usually realize.
What bone grafting is actually trying to accomplish
Bone grafting in implant dentistry is not about replacing the entire jawbone with a block of foreign material. That is a common misconception. The goal is to create a scaffold and biologic environment that allow the patient’s own bone to repopulate an area that is deficient.
Depending on the site and the defect, the graft may help preserve a socket after extraction, widen a ridge, increase vertical height, support the sinus floor, or repair a dehiscence around an implant at the time of placement. Sometimes the objective is modest, such as preserving contour so the final crown emerges naturally through the gum. Other times the goal is structural, such as building enough bone to place an implant where there is currently no stable support.
This distinction matters because not every graft is equally demanding. A small socket preservation and a major vertical ridge augmentation are both called bone grafts, but they differ dramatically in complexity, healing time, cost, and risk.
When grafting becomes necessary
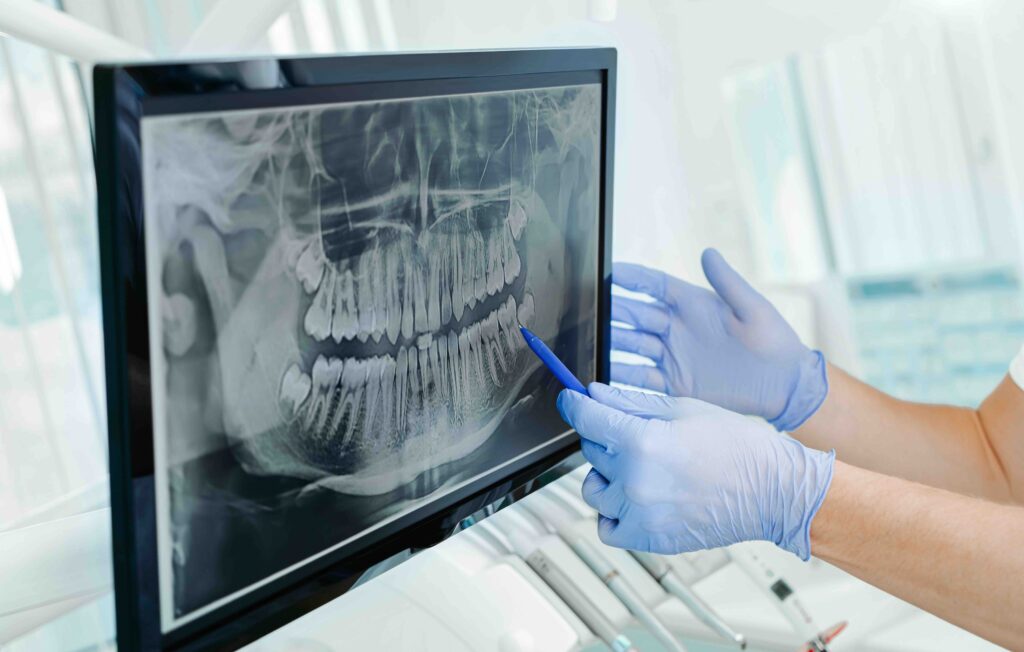
A well-trained implant clinician does not recommend grafting on instinct alone. The decision is usually based on clinical examination, three-dimensional imaging, soft tissue assessment, and restorative planning. That last point gets overlooked. The question is not simply whether an implant can be placed somewhere in the bone. The question is whether it can be placed in the right position for a functional, cleanable, esthetic restoration.
There are several common situations where grafting enters the conversation. One is immediate concern after extraction. If the socket walls are damaged or thin, preserving the site can prevent more serious loss later. Another is delayed treatment, where a missing tooth has been left untreated for years and the ridge has narrowed substantially. Posterior upper implants are another frequent example because the sinus often limits available vertical bone. Patients who have worn removable partials or complete dentures for a long time can also show extensive resorption.
Periodontal history matters too. A tooth lost to chronic infection often leaves behind bone damage that does not fully repair on its own. Trauma can be even more unpredictable. A young adult who lost an upper front tooth in a sports injury may present with a visible collapse of the labial plate, which affects both implant stability and appearance.
The most common grafting approaches in implant dentistry
Clinicians use several approaches, and the right one depends on anatomy, timing, and treatment goals. Socket preservation is among the most common. After extraction, graft material is placed into the socket, often with a membrane over it, to reduce collapse during healing. It does not freeze the ridge in place, but it can significantly improve the site compared with extraction alone.
Guided bone regeneration is another widely used technique. Here, particulate graft material is placed where bone is lacking and covered with a barrier membrane that protects the area from fast-growing soft tissue cells. This creates a protected space where slower-forming bone can develop. It is often used around implants or to widen a narrow ridge.
In the upper jaw, sinus augmentation is a routine solution when there is not enough vertical height beneath the sinus. Some cases require a lateral window approach, where the sinus membrane is gently elevated and graft material is placed beneath it. Milder cases can sometimes be managed with a transcrestal technique through the implant site itself. The concept sounds intimidating to patients, but in experienced hands it is a standard procedure.
Block grafting is more involved. It uses a solid piece of bone, often secured with small fixation screws, to rebuild larger defects. This may be harvested from the patient or obtained from processed donor bone, depending on the case and the surgeon’s preference. It is generally reserved for more substantial deficiencies where particulate graft alone would not provide enough structural support.
What graft materials are made of
Patients often ask whether the graft is “their own bone” or “synthetic.” The answer varies. Each category has strengths and trade-offs, and much of implant surgery is about matching the material to the defect.
Autogenous bone, meaning bone harvested from the patient, is still considered highly effective because it contains living cells and growth factors, and it integrates well. It may be collected from nearby areas in the mouth or, in larger cases, from extraoral sites, though that is less common in routine implant practice. The downside is obvious: a second surgical site increases morbidity.
Allograft is human donor bone that has been processed for safety and medical use. It is common in everyday implant grafting because it is readily available and avoids a donor-site surgery. Xenograft comes from another species, usually bovine, and is also widely used. It tends to resorb slowly, which can help maintain volume in certain situations. Alloplasts are synthetic materials, such as calcium phosphate-based products, designed to support bone growth.
No material is magic. Success depends not only on what is placed, but on blood supply, defect shape, membrane stability, soft tissue closure, infection control, and patient factors such as smoking or poorly controlled diabetes. A perfect graft material will still fail if the biology and mechanics are wrong.
Timing matters more than patients expect
One of the most important decisions in Dental Implants treatment is when to graft and when to place the implant. In some cases, both can be done together. In others, staging is wiser.
If an extraction socket is intact and infection is minimal, a surgeon may place an implant immediately and graft the small gaps around it. That approach can reduce treatment time and preserve tissue contours, especially in selected esthetic cases. However, immediate placement is not universally better. It demands careful case selection. Primary implant stability must be achievable, and the soft tissue must be manageable.
In contrast, if the site has severe infection, a missing bony wall, or extensive collapse, it may be safer to graft first, allow several months of healing, then place the implant into a more mature foundation. This staged approach takes longer but often increases predictability.
Patients tend to focus on speed. Surgeons tend to focus on stability. Those priorities are not always aligned, and that tension is where good judgment matters most.
How healing works after a graft
Bone grafts do not simply “turn into bone” overnight. Healing is gradual and biologically complex. The grafted site needs to stabilize, become vascularized, and serve as a scaffold for new bone formation. Some materials resorb faster, some linger longer, and most healing sites contain a mixture of new native bone and residual graft particles when re-entered.
A small socket preservation may heal sufficiently in roughly three to four months, though timing varies. A larger ridge augmentation often needs longer, commonly four to six months or more. Sinus grafts can fall into a similar range, depending on how much height needs to be built and whether implants are placed at the same time.
Patients often feel fine long before the site is truly ready. That can create the false impression that the area has healed completely. Soft tissue closes faster than bone matures. A gum surface that looks normal may still be covering an immature graft beneath.
What the procedure is like from the patient’s side
Most routine grafting for implants is performed under local anesthesia, sometimes with oral sedation or IV sedation depending on complexity and patient anxiety. The actual discomfort during the procedure is usually minimal because the area is numb. The better question is what the first week feels like afterward.
For small grafts, patients often describe swelling, tenderness, and a sense of pressure more than sharp pain. Sinus procedures can add fullness in the cheek or mild congestion. Block grafts and larger augmentations are more noticeable and generally require more downtime. Bruising is not unusual. Sutures are usually present for at least a week or two.
The postoperative instructions matter. A graft site is less forgiving than many patients realize. Excessive rinsing, poking the area with the tongue, wearing a removable appliance too soon, smoking, or creating pressure with forceful nose blowing after a sinus graft can compromise healing. Most failures are not dramatic. They begin with small disturbances in stability or wound closure.
A patient once described a socket graft as “easier than the extraction and more annoying than painful,” which is a fair summary of many straightforward cases. The bigger grafts are a different category. They require a more serious conversation before treatment begins.
Risks, limitations, and realistic expectations
Bone grafting has a strong track record in modern implant dentistry, but it is not guaranteed. Grafts can resorb more than expected. Membranes can become exposed. Infection can occur. Sinus membrane perforation is a known intraoperative complication in sinus augmentation, though it can often be managed. In larger grafts, partial loss of the grafted volume is a practical concern even when the case still ends successfully.
There is also a more subtle limitation: a graft may create enough bone for an implant, yet not fully restore the original anatomy. That point is especially important in the esthetic zone. Rebuilding hard tissue does not always recreate the exact natural contour that existed before tooth loss. Soft tissue thickness, smile line, adjacent teeth, and lip dynamics all influence the final appearance.
This is where honesty matters. Not every severe defect can be made to look as if nothing ever happened. Sometimes the treatment goal is excellent function and a respectable appearance, not perfection under high magnification and bright overhead lighting.
Bone grafting and esthetics in the front of the mouth
The front teeth deserve special attention because millimeters show. A patient missing a lower molar can often tolerate slight contour differences that would be unacceptable at an upper central incisor. In the anterior maxilla, bone supports the gum architecture. If the labial plate is lost, the overlying tissue can flatten or recede. That affects not only implant stability but also papilla height, emergence profile, and symmetry with the natural tooth on the other side.
This is why surgeons sometimes recommend grafting even when there seems to be enough bone to “fit” an implant. They are planning for where the restoration must emerge and how the tissue will frame it. A narrow implant placed too far palatally in a compromised ridge may technically integrate, yet still produce a long-looking crown or a gray shadow through thin tissue.
These cases often benefit from earlier intervention. Preserving the socket at extraction, managing soft tissue carefully, and avoiding prolonged ridge collapse can make a dramatic difference later.
The cost question, and why cheap treatment can become expensive
Bone grafting adds cost to implant treatment. There is no point pretending otherwise. The fee reflects materials, surgical time, imaging, follow-up, and the additional expertise needed to manage the site properly. For patients already stretching to afford implants, that extra layer can be frustrating.
Yet skipping a necessary graft can cost more in the long run. An implant placed in inadequate bone may fail to integrate, end up in the wrong restorative position, or require correction later. Revision surgeries are more expensive emotionally and financially than getting the foundation right the first time.
That does not mean every recommendation is automatically essential. Thoughtful patients should ask why the graft is needed, what problem it solves, whether there are alternatives, and what happens if it is not done. Good clinicians welcome those questions because the answer should be grounded in anatomy and treatment planning, not vague language.
When grafting may not be the best path
Not every patient with low bone volume is best served by a graft. Sometimes alternatives make more sense. A short implant, a narrower implant, a change in implant number or position, or a bridge may avoid the need for major augmentation in selected cases. In full-arch treatment, angled implants or other designs may reduce the need for extensive grafting, depending on the anatomy and the system used.
Medical history also affects the recommendation. Heavy smoking, poorly controlled diabetes, active periodontal disease, certain medications that influence bone metabolism, and a history of head and neck radiation can all complicate healing. These factors do not always rule out grafting, but they can change the risk profile. In some patients, a simpler restorative solution may be more prudent than a heroic surgical plan.
The best treatment is not the most ambitious one. It is the one that balances biology, function, esthetics, cost, and patient reliability.
Questions worth asking before agreeing to treatment
A productive implant consultation often turns on the quality of the questions. Patients do not need to master graft materials or interpret CBCT scans, but they should understand the rationale behind the plan. A few questions usually bring the picture into focus:
- How much bone is missing, and in what dimension?
- Is the graft intended to preserve the site, allow implant placement, or improve esthetics?
- Can the implant be placed at the same time, or is a staged approach safer?
- What are the main risks in my case?
- What changes if I choose not to graft?
The answers should sound specific, not generic. “You need more bone” is not enough. A better explanation might be that the ridge is too narrow on the facial side to place the implant in a prosthetically correct position without risking thread exposure or future recession. That level of detail signals real planning.
What experienced clinicians watch for
Much of successful grafting comes down to details invisible to patients. Soft tissue management is one. If a surgeon cannot achieve stable closure over a larger graft without tension, the chance of exposure rises. Defect morphology is another. A contained defect with surrounding bony walls behaves far better than an open, non-contained one. Blood supply, membrane choice, fixation, flap design, and the pressure from a temporary prosthesis all matter.
There is also the question of restraint. Some of the best Dental Implants Oaks Dental surgical decisions are decisions not to overbuild. A modest, well-protected graft that heals predictably is often better than an aggressive augmentation done in anatomy that cannot support it. Experience teaches respect for biology. Bone can be encouraged, supported, and guided. It cannot be bullied.
The bigger picture
Bone grafting plays a foundational role in Dental Implants because implants are not placed into empty space or good intentions. They are placed into living tissue that has to heal, integrate, and carry load for years. When that tissue is inadequate, grafting is often the bridge between a compromised site and a stable result.
For patients, the key is understanding that grafting is not separate from implant treatment. It is part of creating a site where the implant has a fair chance to succeed. Sometimes that means preserving bone at the moment a tooth is removed. Sometimes it means rebuilding what has been lost over time. Sometimes it means recognizing that the simplest path is not the shortest one.
Done well, bone grafting is less about adding material and more about restoring possibility. It gives the jaw a second chance to support a tooth replacement that looks right, functions properly, and lasts. That is why it remains one of the most important tools in modern implant dentistry.
Oaks Dental
5000 Parkway Calabasas Suite 308
Calabasas, CA 91302, United States
+1 818-431-2000
FAQ About Dental Implants
What is the downside of a dental implant?
Implants require surgery and a healing period that can last several months. Possible complications include infection, nerve or sinus injury, damage to nearby teeth and failure to bond with bone. Your dentist should assess your health, bone support and alternatives before recommending treatment.
What do dental implants typically cost?
There is no single price for every implant case. The number of teeth replaced, implant components, final restoration and any grafting or extractions affect the total. Request a written estimate covering every stage and confirm insurance benefits and out-of-pocket costs with the practice.
How long do tooth implants last?
An implant can provide long-term support and may last a lifetime with good oral hygiene and regular dental care, but this is not guaranteed. The crown or other restoration may need replacement sooner. Smoking, gum disease and some health conditions can reduce implant success.